
Carbohydrate is not one target
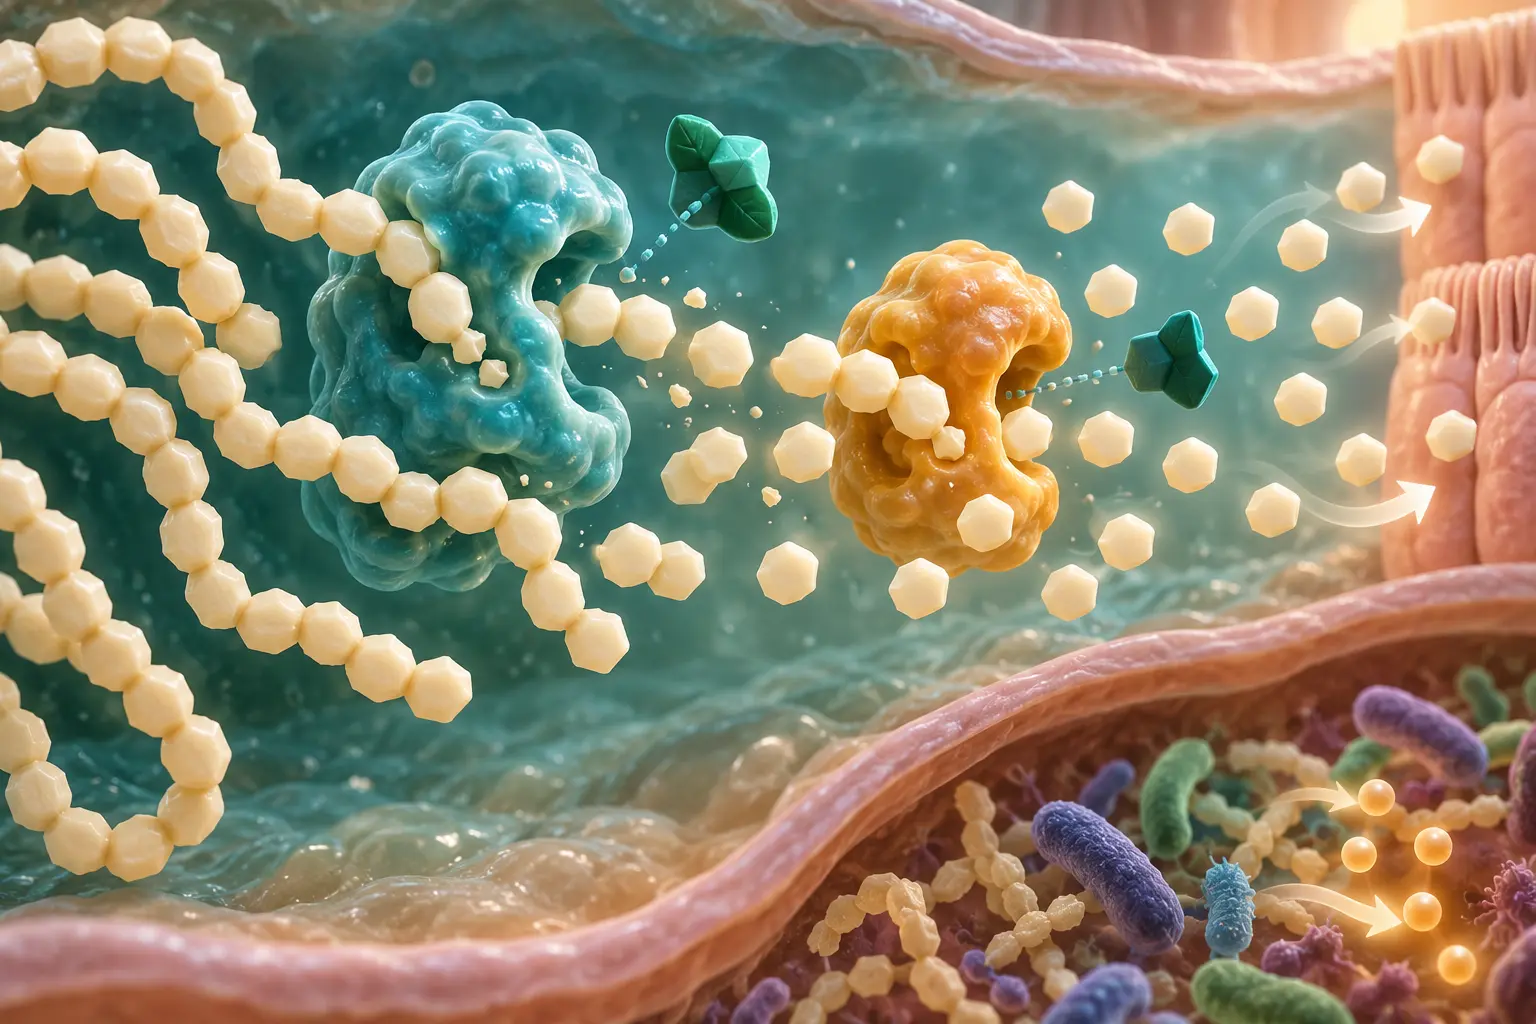
Starch is a chain of glucose units. Enzymes including alpha-amylase and brush-border alpha-glucosidases break digestible carbohydrate into smaller sugars that can be absorbed. Simple sugars do not require the same initial starch-breaking step. Fiber follows different routes and some reaches the colon for fermentation.
An ingredient that inhibits one enzyme cannot be described accurately as blocking all carbohydrate absorption. The effect depends on the substrate in the meal, timing, formulation, dose, and whether the ingredient remains active in the digestive environment. A test-tube result provides a mechanism hypothesis, not a personal calorie deduction.
Do not merge three unlike categories
A smaller glucose rise is not automatically fat loss
A study may measure post-meal glucose, enzyme activity, breath gases, stool energy, appetite, or body weight. These are not interchangeable. Slower digestion can change the shape of a glucose response without eliminating total absorption. More carbohydrate reaching the colon may be fermented, producing gas and metabolites rather than simply vanishing.
For a weight claim, look for randomized trials lasting long enough to measure body-weight or fat-mass differences. Ask whether diet advice was equal, the extract and dose match the sold product, withdrawals were reported, and the difference from placebo was practically important.
Example: the pasta “insurance policy”
A person takes a carb-blocker capsule before pasta and dessert, then logs neither because the package mentions starch control. The dessert contains sugars not addressed by an alpha-amylase claim, and the supplement has no transparent evidence showing that the entire meal becomes non-caloric. The estimate is now less accurate, not more.
A practical alternative is to choose a satisfying pasta portion, include protein and vegetables, and judge the weekly pattern. If glucose control is the concern, use clinician-directed monitoring and treatment rather than borrowing claims from prescription medicines.
Build an evidence record before deciding
Create a one-page record with four columns: the label claim, the exact ingredient and daily amount, the best matching human evidence, and what remains unknown. Copy amounts from the Supplement Facts panel rather than promotional graphics. Include every source of caffeine and any proprietary blend whose individual amounts cannot be determined. When the sold formula changes, the old record no longer describes the current product.
For each study, write the intervention, comparison group, duration, participant type, absolute difference in the outcome, uncertainty, withdrawals, and reported adverse events. Mark whether the research tested the finished product, the same ingredient form, a different extract, a prescription medicine, or only a proposed mechanism. This prevents a strong study on one intervention from becoming borrowed proof for another.
Then create three possible decisions. Reject when the formula, dose, evidence, seller, or safety information is too uncertain. Defer when a medicine review, blood-pressure check, baseline period, or clearer label is needed. Test cautiously only when the expected benefit is modest, the product fits the evidence, risks are acceptable, and stopping rules are defined. A test is not permission to increase the dose, combine products, or ignore symptoms.
Review the whole outcome, not only body weight. Track sleep, hunger, digestion, mood, resting symptoms, training, daily movement, food adherence, and cost. Compare weekly weight averages and waist over a suitable interval while noting sodium, carbohydrate, menstrual-cycle context, constipation, illness, and travel. If the routine improves but the product contribution cannot be isolated, say so. If side effects appear without a meaningful benefit, that is a negative result even when the scale briefly falls. The purpose of the record is not to prove the purchase was worthwhile; it is to make the decision reversible, evidence-led, and resistant to advertising.
Use the five-part claim test
- Name the exact mechanism. “Fat burner” is a marketing category. Identify whether the claim concerns lipase inhibition, starch digestion, appetite, caffeine, thermogenesis, or another pathway.
- Match the exact ingredient and dose. Evidence for a prescription medicine, isolated extract, or studied dose cannot be transferred to a different supplement blend.
- Find the relevant outcome. A laboratory enzyme change, breath measurement, appetite rating, or brief rise in expenditure is not the same as a meaningful change in fat mass or body weight.
- Read the comparison. Check duration, population, diet and activity support, placebo, withdrawals, funding, adverse events, and the absolute difference between groups.
- Test the finished product. Confirm whether the exact sold formula has controlled trials. If amounts or product-level evidence are missing, the honest conclusion remains uncertain.
Write the expected job before buying: what outcome, by what date, compared with what baseline, and what side effect ends the test? This prevents normal water fluctuations or a better week of eating from being credited automatically to the capsule.
Where Fat Burn Active fits
Fat Burn Active should not be described as a carbohydrate blocker unless its exact label, dose, and finished-product evidence demonstrate that effect. A general metabolism claim is not enough.
Fat Burn Active is optional and is not required for fat loss. Its label and finished-product evidence must answer the claim; research on a different medicine or isolated ingredient cannot do that work. Feeling warmer, more alert, less hungry, or seeing a short-term scale change does not prove meaningful fat loss.
Use the Can Fat Burners Block Carbohydrate Absorption? criteria to assess Fat Burn Active rather than relying on a headline claim. Our formula evidence analysis explains the remaining uncertainty. If the product fits your needs, view current availability and ordering terms on the official website. We may earn a commission at no extra cost.
Safety is part of the result
Stop and seek appropriate care for chest pain, fainting, severe palpitations, breathing difficulty, a serious allergic reaction, persistent vomiting or diarrhea, black or bloody stool, jaundice, or severe abdominal pain. A lower scale reading caused by dehydration or gastrointestinal loss is not a successful fat-loss outcome.
Ask a clinician or pharmacist before use if you are pregnant or breastfeeding, under 18, have an eating-disorder history, heart rhythm or blood-pressure problems, diabetes, glaucoma, anxiety, liver, kidney, or gastrointestinal disease, or take prescription or over-the-counter medicines. Avoid combining stimulant products. Supplements do not replace medical obesity treatment, adequate nutrition, movement appropriate to ability, sleep, or follow-up care.
Frequently asked questions
Do carb blockers work on sugar?
An alpha-amylase claim concerns starch digestion, not automatic blocking of all simple sugars.
Can I subtract carbohydrates from my food log?
No reliable personal subtraction follows from a supplement label. Log the meal normally.
Why can carb blockers cause gas?
More undigested carbohydrate may reach the colon, where microbes ferment it.
Sources
- NIH ODS: Dietary Supplements for Weight Loss
- FDA: Precose prescribing information
- Systematic review of Phaseolus vulgaris extracts and weight
- NIDDK: Insulin, Medicines, and Other Diabetes Treatments
Sources reviewed September 13, 2026. This article is general educational information, not medical advice, diagnosis, or treatment.