
Why warmth has many possible causes
Sensation is not calorimetry
Researchers estimate energy expenditure with tools such as indirect calorimetry. A participant’s report of warmth cannot substitute for oxygen and carbon-dioxide measurements, and even a statistically detectable acute change needs an absolute value and relevant duration.
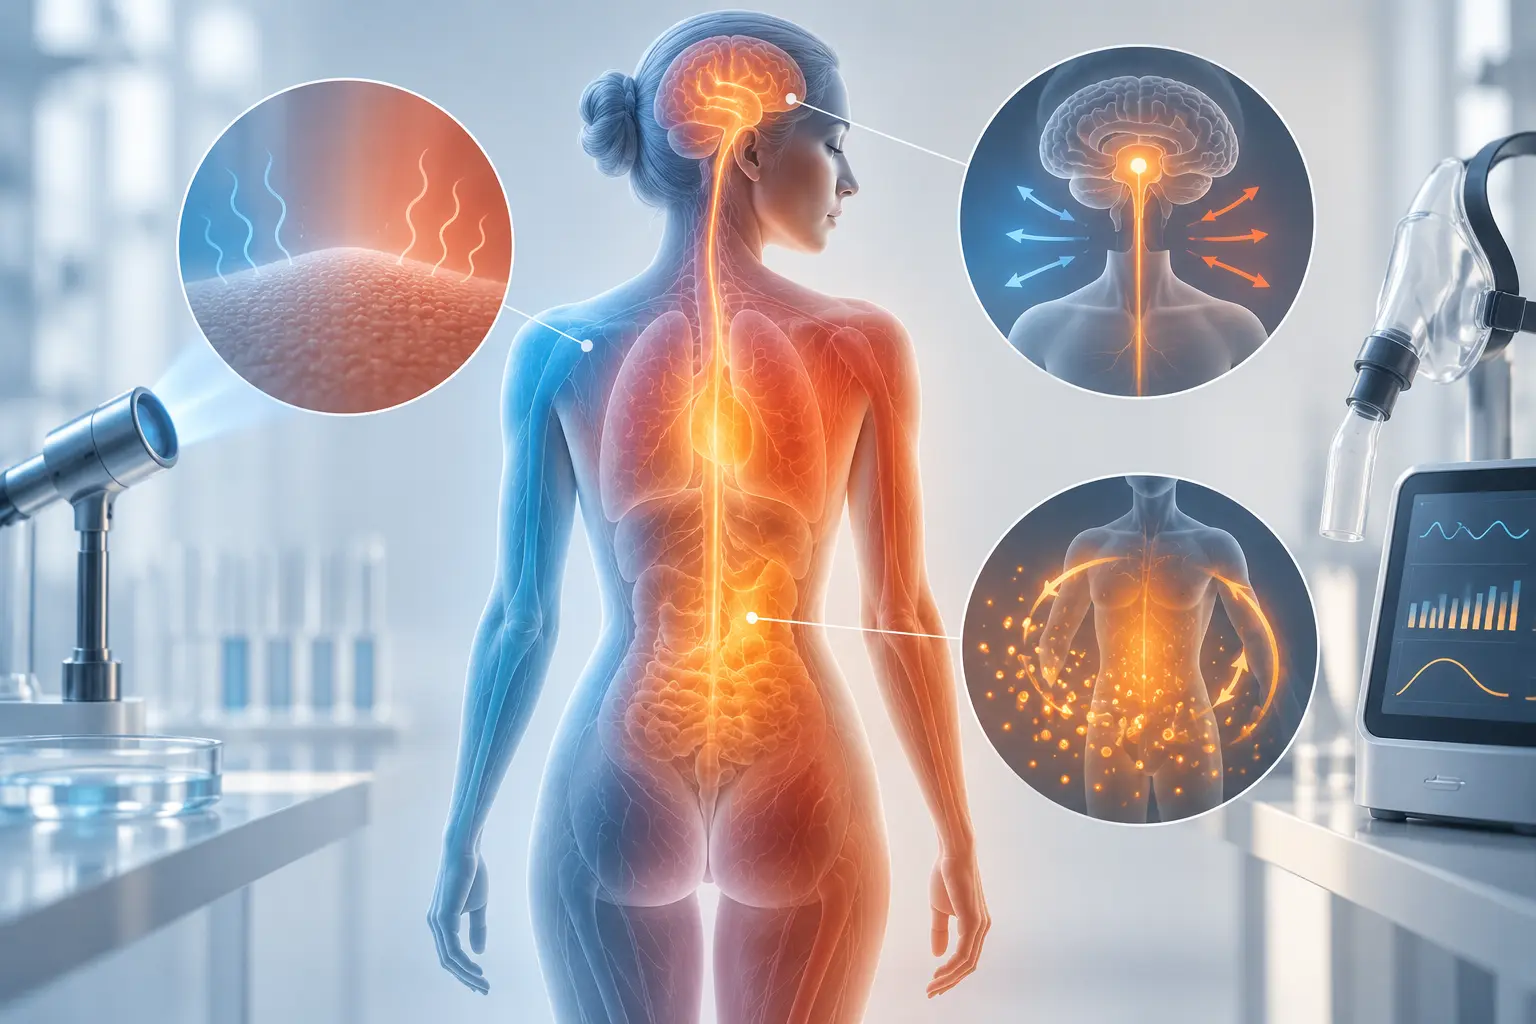
Skin may feel warm because more blood reaches the surface to release heat. Conversely, cold-activated thermogenesis may occur while a person feels cool. Neither sensation reveals net fat balance across the day.
How marketing exploits the signal
“Thermogenic” marketing often compresses a chain of claims: ingredient causes warmth, warmth proves calorie burning, and calorie burning guarantees visible fat loss. Each arrow needs separate human evidence. A flavored capsule can create a strong mouth or stomach sensation while adding little to daily expenditure.
Judge a product by disclosed dose, finished-product trials, absolute outcome, adverse events, and whether the change persists—not by tingling, flushing, sweat, or heart rate.
Example: a hot room and a quiet walk
Leah feels much warmer during a gentle treadmill walk in a poorly ventilated room than during a harder outdoor walk on a cool day. Her perception mainly reflects the setting and heat dissipation. Workout intensity can be assessed with pace, duration, incline, talk test, and heart-rate context; fat-loss progress needs multiweek measurements.
A practical evidence-checking system
- Name the observation. Separate warmth, sweat, a scale change, waist change, energy expenditure, fat oxidation, and fat mass. They are not interchangeable outcomes.
- Check the time scale. Minutes of heat production cannot be projected into months of weight loss without evidence.
- Find the comparison. Ask what happened versus placebo, neutral temperature, the same workout, or the person’s own standardized baseline.
- Use absolute effects. A large percentage increase from a small baseline may still have little practical importance.
- Look for compensation. Hunger, sleep disruption, fatigue, lower spontaneous movement, and adaptation can offset a short metabolic change.
- Track the outcome that matters. Use multiweek average weight, a consistent waist measure, fitness, symptoms, and execution—not intensity of sensation.
Run one change at a time for long enough to interpret it. Keep ordinary meals, fluids, sleep, and movement reasonably stable. Record unusual heat, alcohol, illness, travel, menstrual changes, hard training, and constipation because they can alter measurements without matching fat change.
A useful experiment has a stop rule. End deliberate heat or cold exposure for dizziness, confusion, weakness, chest pain, fainting, severe headache, unusual shortness of breath, or persistent palpitations. People with cardiovascular, neurological, endocrine, kidney, pregnancy-related, or temperature-regulation concerns need individualized clinical advice.
Build a measurement dashboard
Choose one primary outcome and a few supporting measures. If the goal is fat loss, use a four-week trend in standardized morning weight plus a waist measurement taken every two to four weeks. Supporting measures can include meal-plan completion, steps, resistance sessions, sleep opportunity, hunger, and adverse symptoms. Sweat, warmth, tingling, and a single post-workout weight are context, not verdicts.
Use the same scale on a hard surface, similar clothing, and the same waist landmark. Do not tighten the tape to manufacture progress. Photos are optional and should use similar distance, posture, and lighting. If tracking worsens anxiety or restrictive behavior, reduce its frequency and seek appropriate support.
Read research without turning a mechanism into a promise
Start with the population: healthy young adults, people with obesity, trained athletes, animals, or cultured cells. Identify the intervention, dose, temperature, duration, and comparator. Then find the endpoint. Gene expression, tissue temperature, oxygen use, appetite rating, and kilograms of fat are different answers.
Check uncertainty, withdrawals, adverse events, funding, and whether the difference is clinically useful. A statistically significant laboratory signal may be too small or brief to matter. A tightly controlled chamber, cooling suit, scan, or biopsy does not prove that an uncontrolled home routine or retail supplement produces the same effect.
Choose the safer lever first
For most people, dependable levers remain a manageable calorie deficit, adequate nutrition, progressive activity, resistance training, sleep, and an environment that reduces repeated high-effort decisions. These actions also support fitness, strength, blood pressure, glucose control, mobility, and confidence.
Do not add extreme heat, cold, dehydration, or stimulant stacking to make a routine feel powerful. More discomfort does not strengthen evidence. If weight and waist remain unchanged across several documented weeks, audit intake, portions, weekends, movement, sleep, medicines, and health context. Change one plausible variable and set the next review date.
Use a simple decision rule at the review. Continue when the relevant trend improves and the routine remains tolerable. Adjust when execution is consistent but the intended outcome is absent. Stop when harms, cost, or complexity exceed the benefit. Seek professional assessment when symptoms, medicines, rapid unexplained change, disordered eating, or an underlying condition could alter interpretation. This prevents a dramatic sensation from overriding a quieter but more informative record.
Finally, distinguish “possible” from “useful.” Human physiology can produce heat through several pathways, and adipose tissue is biologically active. That does not mean every pathway is large enough, durable enough, or safe enough to become a practical weight-loss intervention. The correct conclusion can be scientifically interesting but clinically modest.
Where Fat Burn Active fits
Fat Burn Active is optional. Its stimulant and botanical ingredients may create alertness, warmth, sweating, or a temporary change in appetite, but those sensations do not demonstrate that the finished product reduces fat mass. Evidence for a mechanism or isolated ingredient cannot establish the effect of the complete formula at the sold dose.
Do not use a thermogenic supplement to chase sweat, heat, dehydration, or a lower post-workout scale reading. Count caffeine from every source and review sleep, anxiety, blood pressure, heart rhythm, medicines, and other supplements. Never combine it with deliberate overheating or use more than the current label directs.
Once the practical steps in Does Feeling Warm Mean You Are Burning More Fat? are working, decide whether an optional supplement adds enough value. Start with the Fat Burn Active review; if the formula and limitations are acceptable, see current availability and official ordering details. We may receive a commission.
Frequently asked questions
Does a warm supplement prove it works?
No. A sensation is not a body-composition outcome.
Does exercise heat mean calories are used?
Exercise uses energy, but warmth cannot quantify it.
Can spicy food raise metabolism?
Small acute effects may occur, but they should not be confused with large fat loss.
When is unusual warmth medical?
Persistent or severe symptoms, especially with fever, palpitations, fainting, or confusion, need assessment.
Sources
- NIH: Human Energy Expenditure
- CDC: Heat and Athletes
- Thermic Effect of Food Review
- NIH ODS: Weight-Loss Supplements
- Human Brown Fat Review
Sources reviewed September 17, 2026. This article is general educational information, not medical advice, diagnosis, or treatment.