
What glucomannan is—and is not
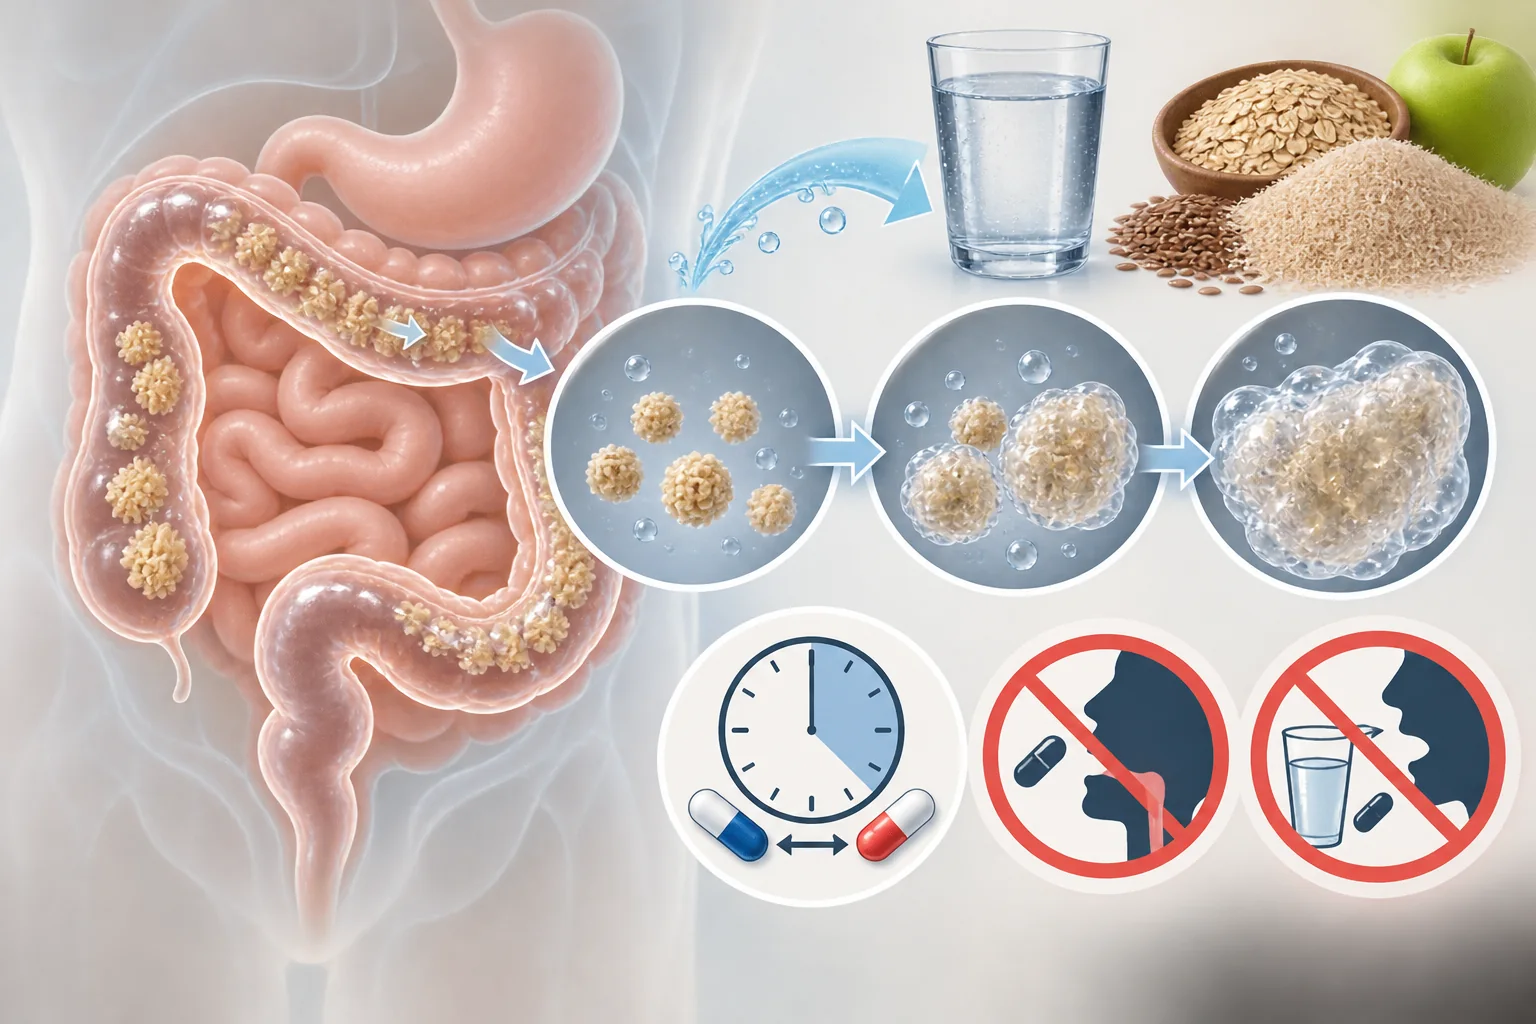
Glucomannan is a fermentable, water-soluble polysaccharide commonly derived from konjac root. Its high viscosity distinguishes it from many non-viscous fermentable fibers. When hydrated, it forms a gel that may increase meal volume and influence gastric or intestinal processing.
It does not neutralize carbohydrate calories already eaten. Marketing that shifts from “supports satiety” to “blocks carbs” changes the claim. Capsule count is also not a dose: two products can use different amounts per capsule and different daily schedules.
Trials do not justify a guaranteed result
A randomized trial in adults with overweight found that glucomannan did not significantly change weight compared with placebo over eight weeks, while gastrointestinal adverse effects were more frequent. Reviews have reached cautious or mixed conclusions because studies are often small, short, and heterogeneous.
The European authorization for a weight-loss claim specifies three grams daily in three one-gram doses before meals with water, in the context of an energy-restricted diet. That wording matters. It does not establish large loss, remove the need for a deficit, or validate products that provide a different exposure.
Find the true dose before judging the product
- Find glucomannan in the Supplement Facts panel, not the advertising panel.
- Record milligrams per serving and convert 1,000 milligrams to one gram.
- Multiply by the number of daily servings on the label.
- Check whether a proprietary blend hides the exact amount.
- Compare the resulting daily grams and timing with the evidence being cited.
- Reject claims that cite a studied dose the product cannot plausibly deliver.
A large capsule bottle can still provide a small daily amount. Do not exceed directions to imitate a study.
Expansion creates real administration risks
Because glucomannan swells, tablets or capsules taken without enough liquid can lodge in the throat or contribute to blockage. Follow the product's full water instructions and warning language. People with dysphagia, structural narrowing, obstruction history, severe motility problems, or unexplained gastrointestinal symptoms should not self-experiment.
Separate oral medicines only according to advice for the specific medicine, because altered absorption and timing may matter. Monitor glucose with professional guidance if diabetes treatment is involved. Stop for swallowing difficulty, chest discomfort, persistent vomiting, severe pain, or inability to pass stool or gas.
When the experiment is not worth running
Skip glucomannan if regular high-fiber meals already control hunger, if the schedule is too complicated, or if past gel-forming fibers caused significant symptoms. A food-based snack or a more substantial meal may be safer and more useful. Cost per evidence-aligned daily dose also matters.
If testing it, predefine success: fewer unplanned snacks without worsening digestion over two to four weeks. Scale change alone is too noisy, and a result during simultaneous calorie cuts cannot isolate the fiber's contribution.
One more decision check
Powders, capsules, and foods are not interchangeable merely because their labels name konjac. Delivery form changes hydration and administration risk.
Interpret the result without overclaiming
Separate the mechanism, the measured outcome, and the decision. A fiber may absorb water or ferment in a laboratory, change a short appetite rating in a controlled meal, yet produce no detectable difference in long-term body weight. Each claim requires its own evidence. Also distinguish statistical significance from a change large enough to matter in everyday eating.
Use weekly weight averages under consistent conditions and compare at least one behavioral outcome, such as unplanned snacks or portion size. Waist measurements can add context, but they also contain measurement error. Do not declare success after a dehydrated weigh-in or failure after a salty restaurant meal.
Keep energy intake, protein, activity, and meal timing reasonably stable during a personal test. Record adherence honestly. If the fiber replaces a higher-calorie food, that substitution may explain the benefit; if it is added to the existing diet, it may add cost without changing intake. Neither pathway makes the result invalid, but it changes what the result means.
Finally, ask whether the intervention is maintainable. A modest benefit that requires unpleasant symptoms, complicated timing, or an expensive daily product may be less useful than a simpler food change. Evidence informs the choice; it does not eliminate personal constraints.
A practical fiber-testing system
- Define the problem. Choose one outcome: meal hunger, stool regularity, food quality, or a weight trend. A vague goal makes every sensation look meaningful.
- Record a seven-day baseline. Note meals, fluids, bowel symptoms, medicines, hunger before and after meals, and weekly average weight.
- Change one variable. Add one food or product at the lowest practical amount. Do not introduce several fibers, a new diet, and a supplement together.
- Increase gradually. Hold each step long enough to assess gas, pain, stool changes, and appetite. More is not automatically better.
- Review after two to four weeks. Compare the chosen outcome, tolerance, cost, and adherence with baseline.
- Keep only useful changes. A fiber strategy should improve the diet or solve a defined problem, not create a permanent ritual without benefit.
Example: separate a real effect from wishful thinking
Alex adds a fiber product, begins meal prep, replaces sweet drinks, and walks after dinner on the same Monday. Hunger and weight improve, but the product cannot receive all the credit. A cleaner test would keep the established routine stable, add one fiber intervention, and compare weekly averages rather than the next morning's scale.
He also records discomfort and skipped doses. If the plan works only on perfect weekdays, its practical effect is smaller than the label suggests. This simple record protects against both exaggerated enthusiasm and dismissing a useful tool too quickly.
Where Fat Burn Active fits
Fat Burn Active is optional and is not a substitute for fiber-rich food, adequate fluid, an appropriate calorie gap, or clinical care. Ingredient evidence does not prove that the complete formula will reproduce the same effect, and a stimulant sensation is not evidence of fat loss.
Once the practical steps in Glucomannan for Weight Loss: Evidence, Dose, and Risks are working, decide whether an optional supplement adds enough value. Start with the Fat Burn Active review; if the formula and limitations are acceptable, see current availability and official ordering details. We may receive a commission.
Frequently asked questions
Does more fiber always mean more weight loss?
No. Fiber can support fullness, food quality, or regularity, but body-fat change still depends on sustained energy balance. Extra fiber can also add discomfort without improving intake.
How quickly should I increase fiber?
Increase gradually and assess tolerance. Sudden large changes commonly cause gas, bloating, cramps, or altered stools. Fluid needs and the safest pace vary.
Can fiber replace vegetables and whole foods?
No. An isolated fiber may provide a specific physical effect, but whole foods also provide protein, micronutrients, water, and diverse plant compounds.
When should I seek medical advice?
Get advice for swallowing difficulty, bowel narrowing or obstruction history, severe or persistent pain, vomiting, bleeding, unexplained weight loss, major bowel changes, pregnancy, or complex medicine schedules.
Sources
- NIH ODS: Weight-Loss Supplements
- Randomized Trial of Glucomannan
- EFSA Scientific Opinion on Glucomannan
- European Union Register of Nutrition and Health Claims
Sources reviewed September 15, 2026. This article is general educational information, not medical advice, diagnosis, or treatment.