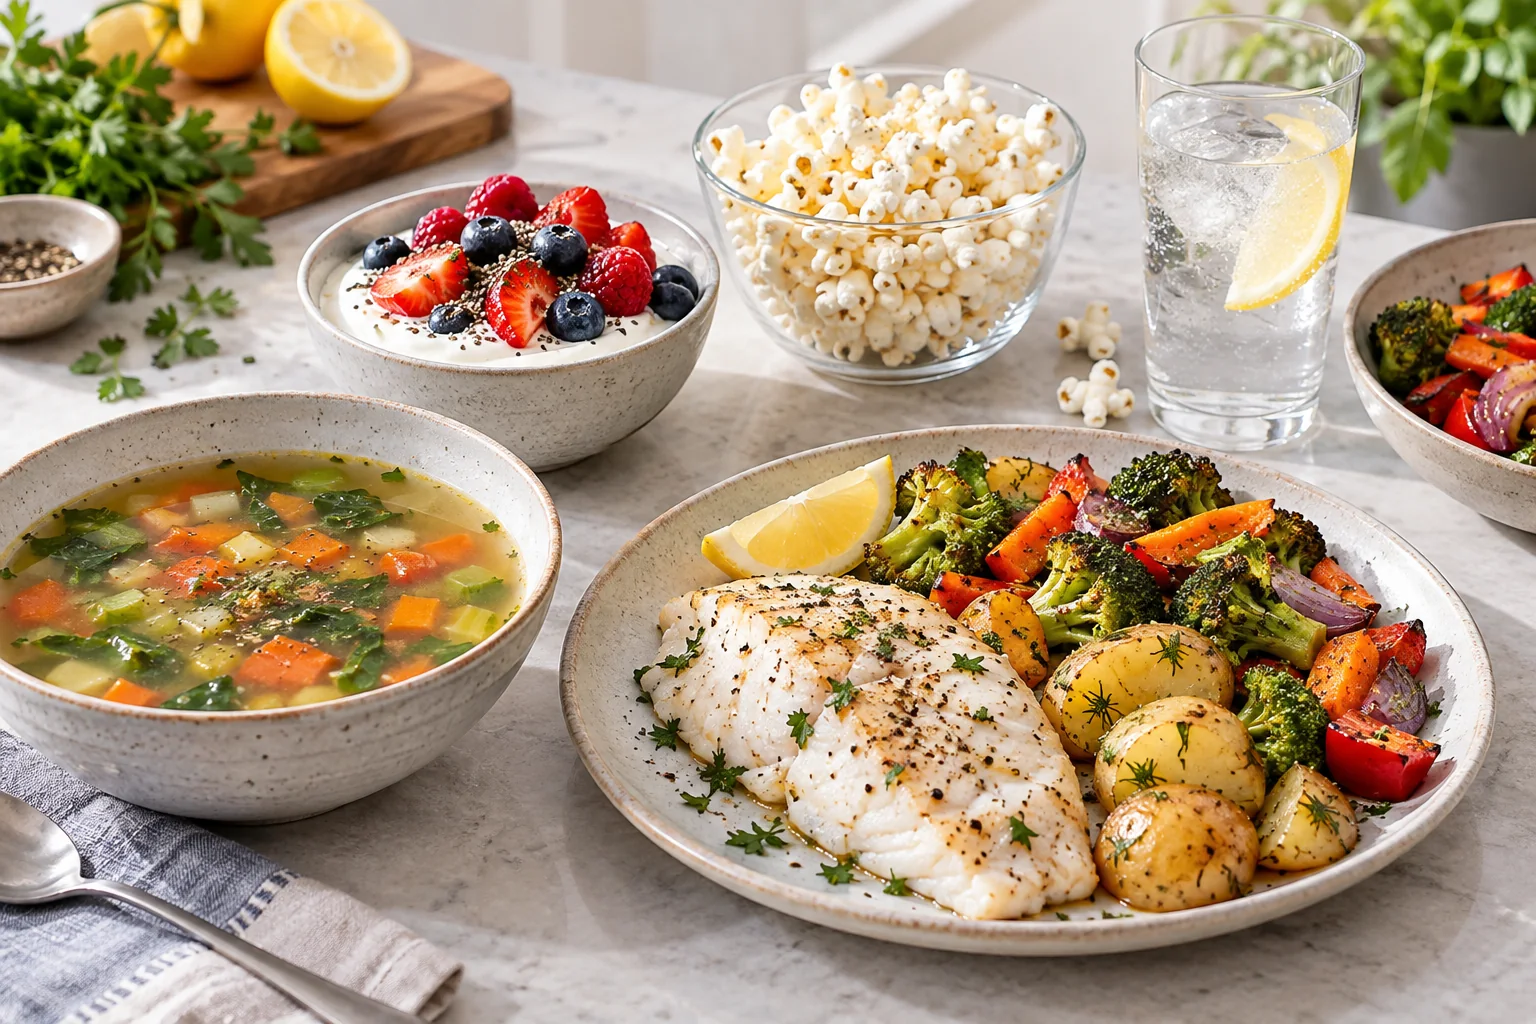
Use a four-factor satiety screen
No score guarantees fullness. Sleep, stress, meal timing and the size of the deficit can outweigh food choice.
Filling options by eating occasion
Meals: broth-based vegetable and bean soup, white fish with potatoes and vegetables, eggs with whole-grain toast and fruit, or a tofu-bean bowl. Breakfast: Greek yogurt with berries and oats, eggs with vegetables, or oatmeal strengthened with a protein source. Snacks: fruit with yogurt, vegetables with hummus, cottage cheese with tomatoes, or a measured portion of popcorn beside protein.
Preparation matters. Frying, heavy sauces and large oil additions can raise energy density quickly. That does not make them forbidden; it means they should be visible in the plan.

Three low-calorie traps
- Too small: the snack delays hunger for twenty minutes but does not solve it.
- Protein-free: vegetables alone become a substitute for a needed meal.
- Diet-product rebound: an unsatisfying substitute leads to both the substitute and the original food.
The correction may be to spend more calories on a complete meal. Sustainable fat loss is not a contest to eat the lowest possible number at every occasion.
Test foods in the setting that matters
Choose one recurring problem—late-afternoon hunger, post-dinner grazing or a weak breakfast. Try one structured option for five to seven comparable days. Record how long it lasts, whether you enjoy it, and what you eat afterward. A food that is filling in a laboratory but inconvenient at work is not your best solution.
Keep the smallest combination that reliably bridges to the next planned meal. If extreme hunger continues, review the overall calorie target, sleep, medications and medical symptoms rather than stacking more “free foods.”
Appetite is a system, not a character test
Hunger is shaped by the size and composition of meals, learned cues, sleep, stress, medications, activity, recent restriction and the food environment. A person can understand energy balance perfectly and still struggle when several of those pressures align. Treating every difficult eating moment as weak willpower hides the part that can actually be redesigned.
Separate three questions. Physiological hunger tends to build gradually and accepts a range of foods. A specific craving is narrower and can appear without an empty-stomach feeling. Loss-of-control eating involves difficulty stopping and deserves more care than another rigid diet rule. These states can overlap; the labels are tools for choosing a response, not diagnoses.
Use a seven-day appetite audit
For seven ordinary days, note the time, what you ate or drank, hunger before and after, sleep duration, stress level and whether the choice was planned. Keep the record brief enough to finish. The goal is not perfect calorie accounting. It is to find a repeated pressure point such as a low-protein lunch, a sweet drink that replaces no food, a late work trigger, short sleep or an easy-to-eat snack kept within reach.
Choose one change for the next week and define it precisely. Examples include adding vegetables and beans to dinner, changing one daily drink, setting a consistent sleep opportunity, portioning a snack before opening the laptop or taking a ten-minute pause after a stressful call. Review average weight only if weight loss is the goal; also review hunger, energy, digestion, food preoccupation and how often the plan was usable.
If the experiment does not help, that is information rather than failure. Change the intervention, not your self-description. A smaller, repeatable adjustment generally teaches more than simultaneously cutting food, adding exercise and buying a stimulant.
When self-help is not enough
Frequent loss of control, binge episodes, compensatory behaviors, severe restriction, intense guilt around food or eating in secret can be signs that specialist support is appropriate. Seek help from a qualified clinician or eating-disorder professional rather than using appetite suppression to cover the pattern. Persistent thirst, unexplained weight change, major fatigue, sleep-apnea symptoms, depression, anxiety or medication-related appetite changes also deserve medical review.
Pregnancy, adolescence, frailty, diabetes treatment and a history of disordered eating require individualized advice. Seek urgent help for chest pain, fainting, severe breathlessness, thoughts of self-harm or another acute concern.
Interpret the result without fooling yourself
Judge the change against a predeclared question. If the intervention was designed to reduce afternoon hunger, compare afternoon hunger and unplanned eating—not the scale the next morning. If it was designed to lower weekly energy intake, review at least two to four comparable weeks and include weekends. Sodium, carbohydrate, bowel contents, menstrual-cycle timing, travel and hard training can move body weight independently of fat.
A useful result can be behavioral even before weight changes: fewer automatic drinks, a slower eating rate, one less late-night eating episode or improved sleep opportunity. Those are leading indicators, not guaranteed outcomes. Keep them only when they make the overall plan easier and nutrition remains adequate.
When nothing improves, check whether the experiment actually addressed the dominant cause. Adding vegetables will not solve sleep deprivation; buying low-calorie drinks will not resolve binge eating; an earlier bedtime will not correct a medication effect. The best next step may be a different environmental change, a less aggressive calorie target or professional assessment. This cause-matching rule prevents an endless stack of generic diet tips.
Where Fat Burn Active fits
A stimulant cannot turn an incomplete snack into a satisfying meal or justify an excessively low calorie target. Fat Burn Active is optional and cannot repair an eating environment, replace sleep or treat emotional eating. Its current official page lists at least 120 mg caffeine per serving from caffeine anhydrous and guarana, additional unquantified caffeine from green-tea extract, and bitter-orange extract standardized to 6 mg synephrine. Feeling more alert or less hungry for a short time is not proof of meaningful fat loss.
A supplement is not required to benefit from Low-Calorie Foods That Are Actually Filling. If your foundations are already in place, use the independent Fat Burn Active review to judge whether the formula has a useful optional role. If it fits your expectations and stimulant tolerance, check current product details and ordering terms. We may receive a commission.
Frequently asked questions
Should hunger disappear during weight loss?
No. Some hunger can occur, but constant, escalating hunger is a reason to review the size of the deficit, meal structure, sleep and medical context.
Does feeling full prove that a meal supports weight loss?
No. Fullness can help adherence, but portions, energy intake, nutrient quality and the longer trend still matter.
Can a supplement replace appetite-management habits?
No. A temporary stimulant effect does not correct sleep loss, emotional triggers, low-volume meals or an environment built around automatic eating.
Sources
- Dietary energy density and behavior
- Portion size and energy density review
- Dietary protein and appetite
- NIDDK: Weight-management treatment
Sources reviewed September 13, 2026. This article is general educational information, not medical advice, diagnosis, or treatment.