Follow the carbon ledger
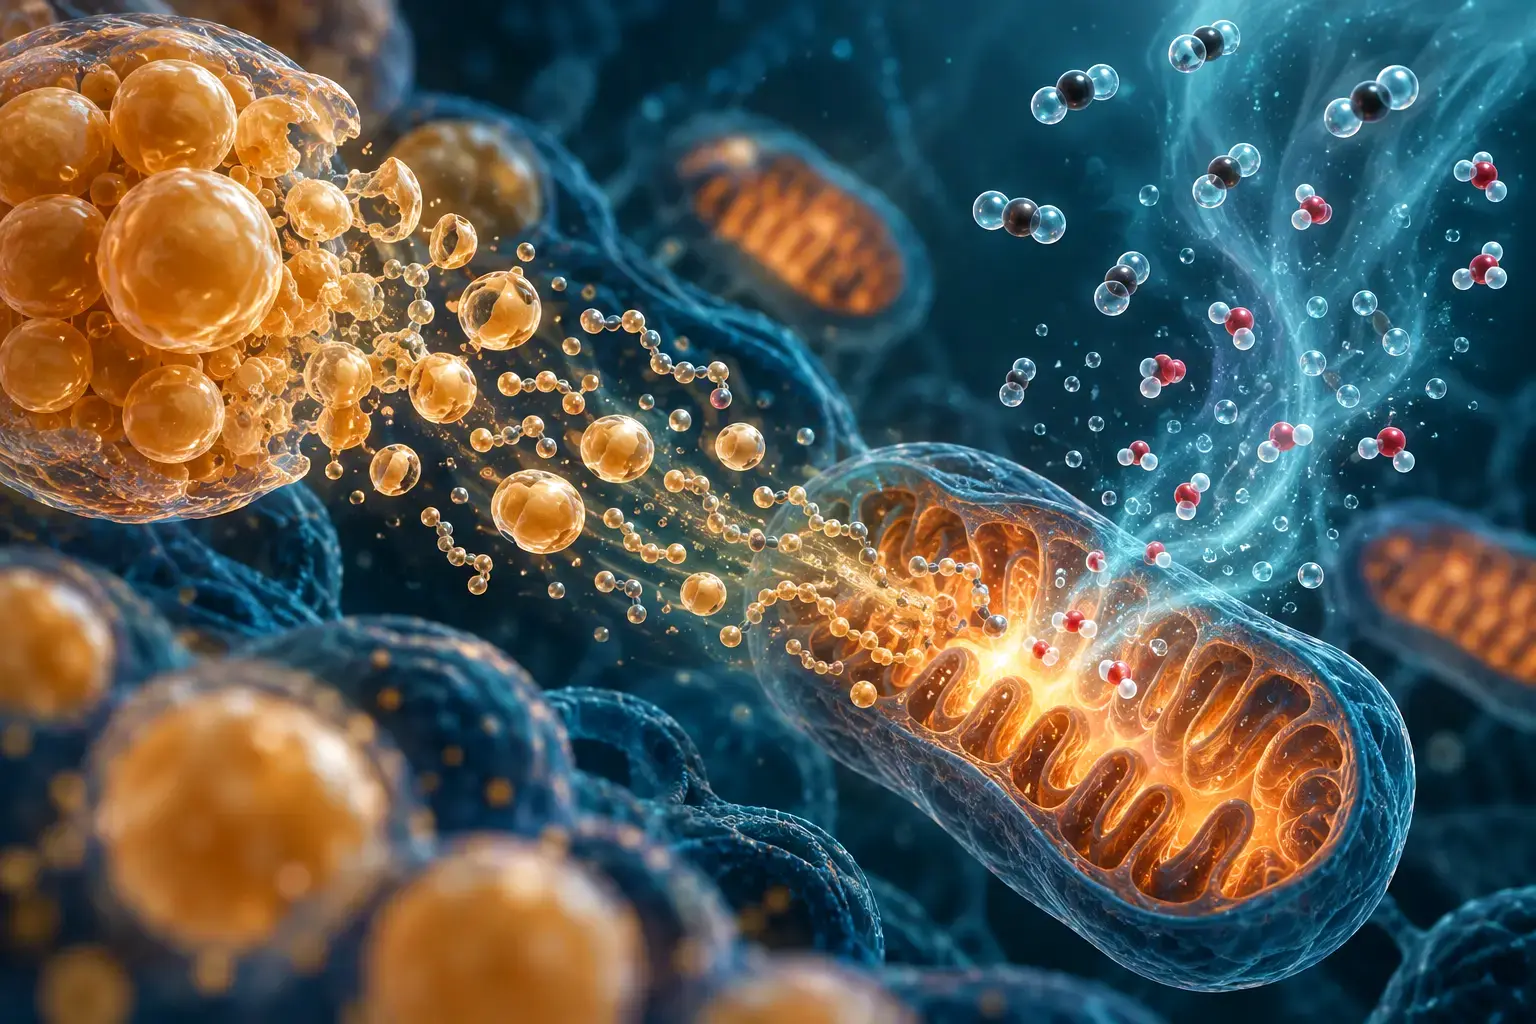
Body fat is stored mainly as triglyceride, built from carbon, hydrogen and oxygen. Conservation of mass means its atoms cannot vanish. Oxidation produces carbon dioxide, water and usable energy captured in molecules such as ATP, with some energy released as heat.
A BMJ mass-balance calculation shows that oxidizing 10 kg of human fat produces about 8.4 kg of carbon dioxide and 1.6 kg of water, while requiring inhaled oxygen. This is chemical accounting, not a rate prediction or advice to breathe more.
From fat cell to final products

Why breathing and sweating are not hacks
Hyperventilating does not command adipocytes to provide carbon; it can disturb blood gases and cause dizziness. Exercise increases breathing because tissues need oxygen and produce carbon dioxide, but body-fat change depends on total fuel use and energy balance over time.
Sweating regulates temperature. A lower post-workout weight is mainly water and reverses with drinking. Saunas and sweat suits do not prove extra triglyceride oxidation.
Do fat cells leave the body?
Most adult adipocytes shrink as the lipid droplet gets smaller; intact cells are not exhaled. Fat does not become muscle. Resistance training may preserve or build muscle while a separate deficit reduces fat.
Released fatty acids can be re-stored if not ultimately oxidized. Mobilization and an acute increase in “fat burning” are not the same as net loss. Audit claims by asking whether research measured heat, fatty-acid release, acute oxidation, body weight, or actual fat mass—and whether it tested the sold formula.
Separate mechanism, measurement, and outcome
Three questions are often collapsed into one. First, can a biological event happen—for example, can fatty acids leave an adipocyte, can glycogen bind water, or can hormones influence depot behavior? Second, can a tool measure that event accurately? Third, does the event produce a meaningful long-term outcome for a person? A plausible mechanism does not automatically answer the measurement or outcome questions.
Give the greatest weight to human research that uses a relevant population, sufficient duration, a comparison group, and a measure that matches the claim. A short experiment measuring substrate oxidation cannot establish months of finished-product fat loss. An association between a hormone and body shape cannot prove that lowering one daily reading will reshape a chosen region. A scale trend cannot reveal which tissue changed without supporting methods.
For supplement claims, match the exact ingredient form and amount, then look separately for evidence on the complete sold formula. Multi-ingredient products can combine uncertain doses, interactions, and stimulant exposure. Testimonials cannot isolate these effects because users frequently change food, activity, sleep, and expectations at the same time.
A 14-day interpretation protocol
- Days 1–3: observe ordinary intake, morning weight, waist conditions, sleep, activity, sodium, carbohydrate pattern, and symptoms without reacting to each number.
- Days 4–10: hold the core routine reasonably consistent. Use comparable weigh-ins and note only major disruptions such as travel, illness, restaurant meals, hard training, or menstrual-cycle changes.
- Days 11–14: calculate two seven-day averages and review behavior before interpreting the direction.
Fourteen days may reveal obvious noise, but it is not always long enough to prove or disprove fat loss. If the expected change is small, menstrual cycles are relevant, or measurements are sparse, continue for another comparable period. Do not respond to an unexplained high day by fasting, dehydrating, doubling exercise, or increasing a stimulant. Those reactions create new noise and can make the plan less safe.
Write the conclusion in cautious language: “the trend is consistent with progress,” “fluid is a plausible short-term explanation,” or “the current data do not show change.” This is more accurate than claiming a single reading proves fat gain, metabolic damage, or supplement success.
How to track the result without fooling yourself
A bathroom scale reports total mass. It cannot separate fat, water, glycogen, lean tissue, bone, organs, or food still moving through the digestive tract. Weigh under comparable conditions—often after waking and using the bathroom, before food—and calculate a seven-day average. Add a waist measurement every two to four weeks, consistent photographs if useful, and a short behavior record covering meals, activity, sleep, travel, hard training, and unusual sodium or carbohydrate intake.
Judge agreement across several weeks. One low reading after sweating and one high reading after a restaurant meal are weak evidence about adipose tissue. If the average, waist, and execution record remain unchanged across three to four well-documented weeks, reassess intake and movement rather than using water as an unlimited explanation. Change one variable and set another review date.
Build the part of the plan you can control
Use a moderate energy deficit that leaves room for adequate nutrition and ordinary life. Build meals around an appropriate protein source, fiber-rich plants, and portions that fit hunger and the goal. Include resistance training to preserve or build capability, accumulate aerobic activity and everyday movement appropriate to health, and protect sleep. These actions affect overall energy balance and health; they cannot order one body region to release fat first.
Faster scale loss is not automatically better. Severe restriction can worsen hunger, mood, recovery, and adherence while producing dramatic water changes that look like proof. Medical conditions, pregnancy, eating-disorder history, and medicines require individualized care. Rapid unexplained weight change, marked swelling, one-sided leg swelling, breathing difficulty, fainting, or severe weakness should be assessed rather than treated as routine diet noise.
Where Fat Burn Active fits
A thermogenic or oxidation mechanism is not finished-product evidence of meaningful long-term fat loss. Fat Burn Active is optional and cannot replace nutrition, activity, sleep, hydration, or medical care. Its current official page lists at least 120 mg caffeine per serving from caffeine anhydrous and guarana, additional green-tea caffeine that is not quantified, and bitter-orange extract standardized to 6 mg synephrine. Warmth, stimulation, sweating, or a short-term scale change cannot prove a finished-product fat-loss effect.
A supplement is not required to benefit from What Happens to Fat When You Lose Weight?. If your foundations are already in place, use the independent Fat Burn Active review to judge whether the formula has a useful optional role. If it fits your expectations and stimulant tolerance, check current product details and ordering terms. We may receive a commission.
Frequently asked questions
Can a home scale identify fat loss?
No. It measures total mass. Multi-week averages, waist, and consistent behavior provide better context.
Does sweating show fat leaving?
No. Sweat primarily changes body water; a lower post-workout number is not a direct fat measurement.
When should a weight change be checked medically?
Seek qualified help for rapid unexplained changes, significant swelling, breathing difficulty, fainting, severe weakness, or symptoms related to disease or medicines.
Sources
- BMJ: When somebody loses weight, where does the fat go?
- PubMed record for the mass-balance paper
- NIDDK: Body Weight Planner
- NIH ODS: Weight-Loss Supplements
Sources reviewed September 13, 2026. This article is general educational information, not medical advice, diagnosis, or treatment.