
What the scale actually measures
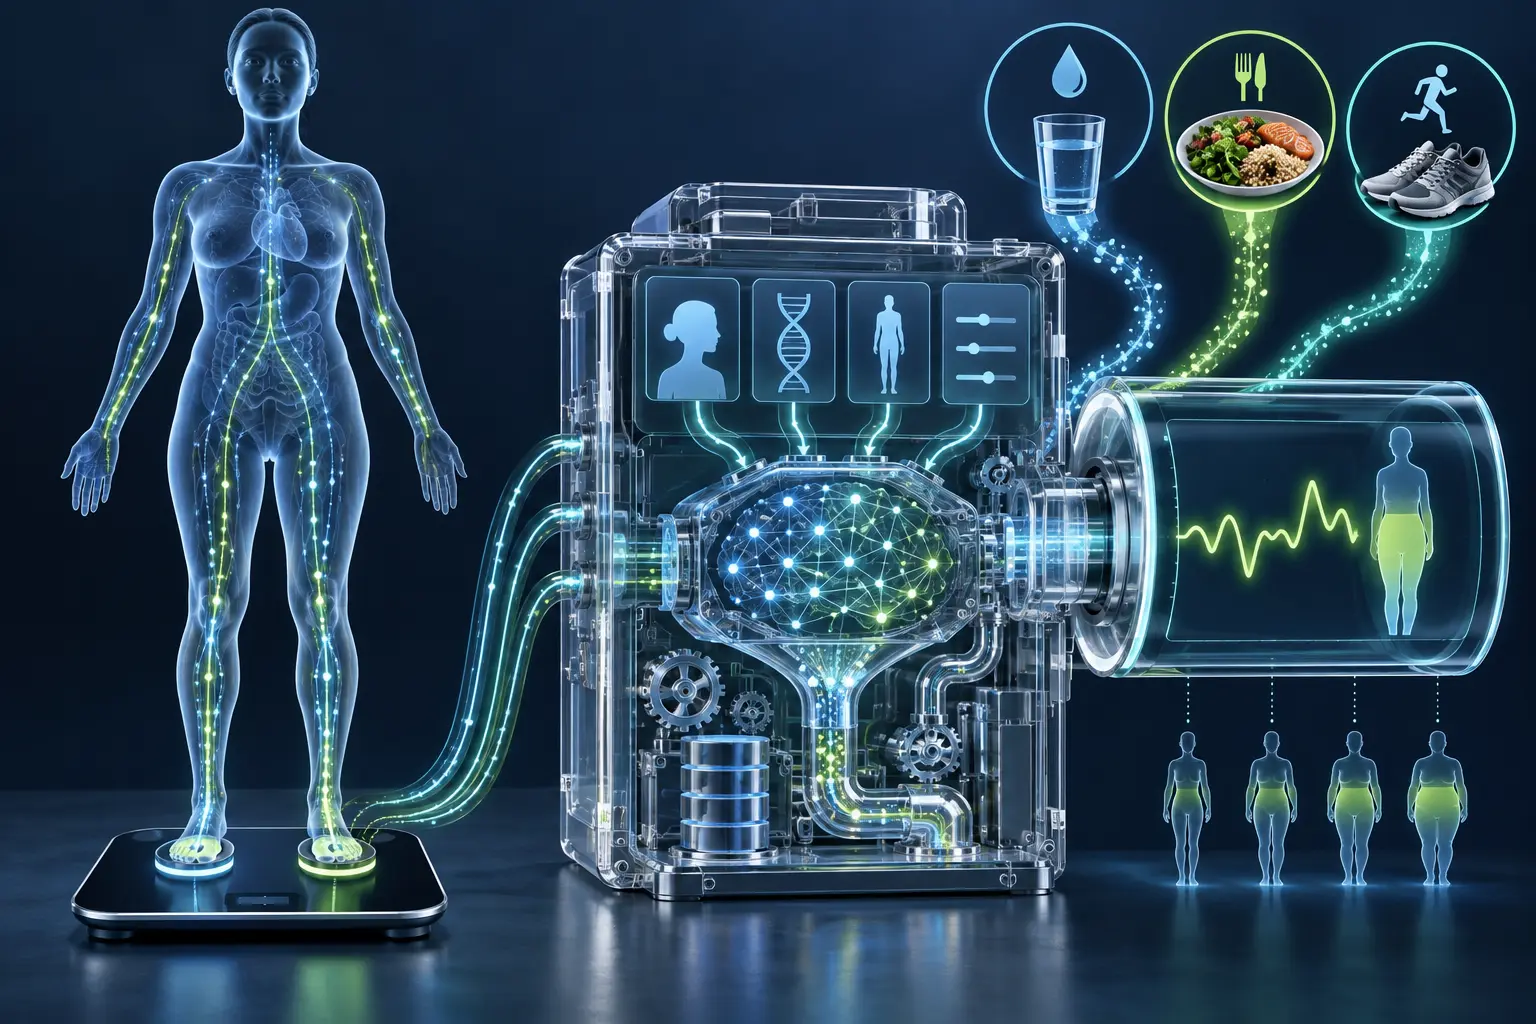
Foot-to-foot bioelectrical impedance analysis sends a small electrical current through the body and measures opposition to that current. Water-rich lean tissue and less-conductive fat tissue influence the pathway differently. The device combines impedance with body weight and profile inputs such as height, age, and sex, then applies a proprietary prediction equation.
The screen therefore contains measured inputs plus model assumptions. Two brands can turn similar electrical data into different percentages. A device may be consistent while still being inaccurate for an individual whose body shape, hydration, ethnicity, training status, age, or health differs from the populations used to build its equation.
Why the percentage moves
Accuracy is not the same as repeatability
In a study comparing three commercially available smart scales with dual-energy X-ray absorptiometry, scale weight was accurate, but body-composition estimates were not. That distinction is crucial. A device can display many decimal places and reproduce similar numbers without being close to a reference measure of fat mass.
Reference methods also have assumptions and error. DXA, air-displacement plethysmography, isotope dilution, imaging, and multi-compartment models answer somewhat different questions and differ in access and cost. No home scale becomes a clinical reference simply because its app draws a smooth graph.
Use a home scale as a standardized trend tool
- Use the same device on the same hard, level surface.
- Measure at a similar time, ideally after using the bathroom and before food, drink, or exercise.
- Keep feet clean and positioned consistently according to the instructions.
- Avoid interpreting a reading after unusual dehydration, a large meal, alcohol, or hard training.
- Review a rolling trend over weeks and pair it with waist, weight, clothing fit, and strength.
- Ignore tiny changes that are smaller than ordinary biological and device variability.
Example: apparent muscle loss after a workout
A person weighs after a long, sweaty session and the app reports less body fat and more lean mass. Two days later, after a salty meal and different hydration, the direction reverses. Neither reading proves rapid tissue remodeling. The inputs to the impedance estimate changed.
They switch to comparable morning conditions and view monthly rather than daily composition trends. Decisions about food and training are based on performance, waist, weekly average weight, and a sufficiently long pattern. If accurate composition matters clinically, they discuss an appropriate validated method with a professional.
Separate observation from interpretation
Record what happened before explaining why. “The seven-day average increased, waist was unchanged, and three readings followed restaurant meals” is an observation. “I gained fat because of sodium” is an interpretation that the measurements alone cannot prove. This distinction prevents a plausible mechanism from becoming a diagnosis.
Before acting, list at least two explanations and the next observation that could separate them. Temporary fluid or digestive mass may settle after ordinary routines resume; a tissue trend is more likely to persist across comparable weeks. Measurement error becomes more plausible when technique, device placement, clothing, timing, or the person taking the measurement changed. Keep uncertainty visible instead of forcing a precise story from limited data.
Set an action threshold in advance. For example, continue unchanged when only one daily reading differs; check technique when duplicate measurements conflict; review the plan when several comparable weekly averages and waist measurements move in an unwanted direction; seek care when concerning symptoms appear. The threshold should reflect the goal and medical context. This approach turns tracking into a decision aid rather than a daily judgment, and it protects useful habits from being rewritten whenever body water, digestion, or a consumer algorithm changes the display.
Use a two-week measurement system
Write the question before collecting more data. Use morning body weight after using the bathroom and before eating or drinking when daily weighing is appropriate. Keep the scale on the same hard surface, calculate a seven-day average, and measure waist no more than weekly at the same landmark. Record only context that can change the interpretation: unusual sodium or carbohydrate intake, bowel pattern, menstrual-cycle phase, travel, alcohol, hard training, illness, medicines, and major schedule changes.
Do not react to each entry. Set a review date fourteen days ahead and keep food, movement, and training reasonably stable unless safety requires a change. At review, compare average weight, waist, clothing fit, adherence, and symptoms. Decide whether the signal is temporary mass, measurement noise, a plausible tissue trend, or something that needs professional assessment. One controlled observation answers more than several simultaneous diet changes.
Where Fat Burn Active fits—and where it does not
Do not attribute a one-day body-fat percentage change to Fat Burn Active. The product and the scale cannot validate each other; both require independent evidence and controlled interpretation.
Fat Burn Active is optional and is not required for fat loss. It cannot identify water retention, clear constipation, validate a tape measurement, or turn a body-fat estimate into a direct measurement. A short-term change after taking any product does not establish that body fat changed.
Once the practical steps in Body-Fat Scales: How Accurate Are They? are working, decide whether an optional supplement adds enough value. Start with the Fat Burn Active review; if the formula and limitations are acceptable, see current availability and official ordering details. We may receive a commission.
Know when the number needs medical context
Seek prompt medical advice for rapid unexplained weight change accompanied by swelling, shortness of breath, chest pain, fainting, severe weakness, persistent vomiting, marked thirst or urination, blood in stool, severe abdominal pain, fever, or inability to pass stool or gas. New symptoms matter more than an attempt to complete a tracking experiment.
Fluid balance and bowel function can be affected by heart, kidney, liver, endocrine, gastrointestinal, and neurological conditions as well as medicines. Pregnancy, an eating-disorder history, diabetes medication, diuretics, obesity medication, and major changes in bowel habits require individualized guidance. Do not use dehydration, laxatives, extreme sodium restriction, or extra exercise to force a lower reading.
Frequently asked questions
Are body-fat scales useless?
No. Weight can be useful, and standardized composition trends may add context, but the percentage is an estimate.
Can they measure muscle gain?
They estimate lean mass rather than directly measuring muscle. Hydration can mimic rapid change.
Which reading should I trust?
Trust comparable long-term patterns more than one reading or extra decimal places.
Sources
- Accuracy of smart scales on weight and body composition
- NIH: Bioelectrical impedance analysis in body composition measurement
- European Society for Clinical Nutrition guidance on bioelectrical impedance
- Review of body-composition assessment methods
Sources reviewed September 13, 2026. This article is general educational information, not medical advice, diagnosis, or treatment.